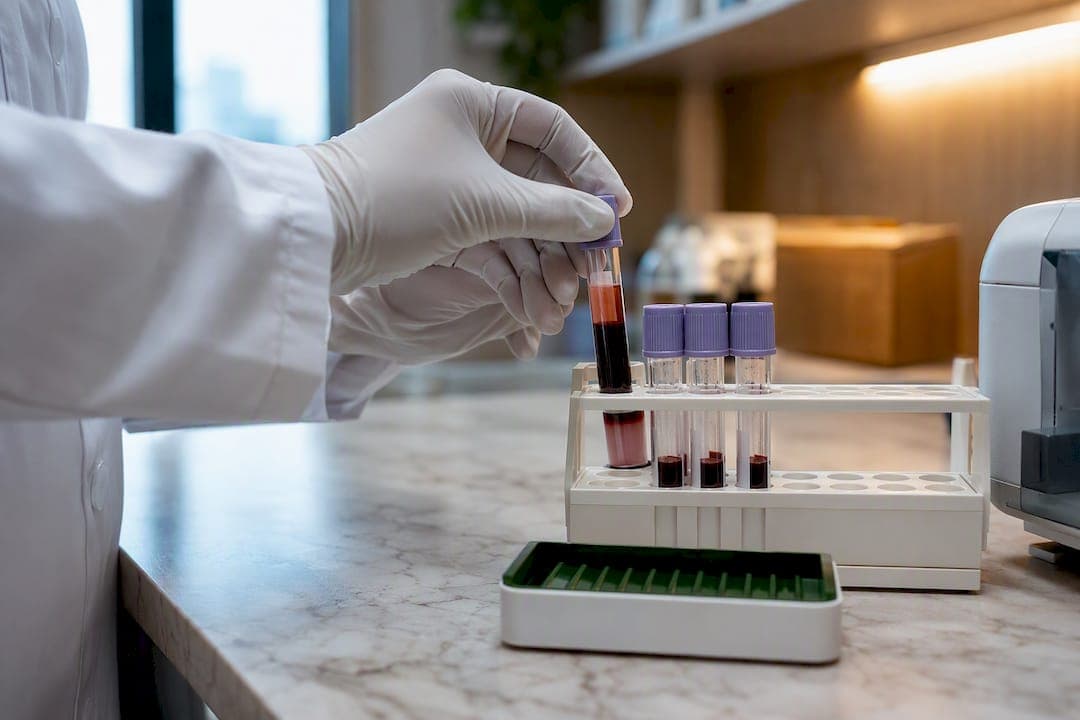
For people with low vitamin D or a higher fracture risk, taking vitamin D3 with vitamin K2 helps to guide calcium into bone rather than into arteries or soft tissue. The evidence is strongest for bone outcomes in people who are deficient or at elevated fracture risk; benefits for the heart and other systems are promising but still mixed. Before starting either nutrient, get your serum 25(OH)D checked and tell your clinician about any blood thinners you take.
TL;DR:
- Supplementing with vitamin D3 is most effective for bone health when blood levels are below 50 nmol/L and accompanied by calcium intake over 800 IU daily.
- Vitamin K2 MK-7's longer bloodstream half-life makes daily dosing more practical and consistent than MK-4, which requires higher doses to have an effect.
- Combining vitamin D3 and K2 enhances bone mineral density and may reduce arterial calcification because K2 activates calcium-regulating proteins produced by D3.
- Evidence from large trials shows no clear benefits of vitamin D supplementation for chronic disease prevention if baseline levels are sufficient, highlighting the importance of testing first.
- Those at higher fracture, deficiency, or calcification risk should get baseline vitamin D and bone health tests before supplementing and consult their healthcare provider about proper dosing.
Table of Contents
- Vitamin D3 K2 Benefits Start With What D3 Does Alone
- Vitamin K2 MK-7 vs MK-4: Why the Form You Choose Matters
- The D3 K2 Synergy: How the Two Vitamins Work as a Team
- What Clinical Trials Actually Show, and Where They Fall Short
- How to Dose D3 and K2: Ranges, Timing, and Safety Checks
- Who Should Test Before Supplementing, and Who Should See a Clinician
- Does D3 K2 Affect Immune Function and Autoimmune Risk?
- Can Vitamin D3 K2 Improve Mood and Cognitive Function?
- Vitamin D3 K2 and Metabolic Health: Insulin Sensitivity and Diabetes Risk
- Why Taking D3 and K2 Together Beats Either Alone
- Garden State Medical Group's Take on D3 and K2 Supplementation
- Get Tested Before You Supplement
- Sources
- FAQ
Vitamin D3 K2 Benefits Start With What D3 Does Alone
Vitamin D3 (cholecalciferol) tells your gut to absorb more calcium and phosphate from food, and it supports the mineralization process that keeps bone dense. Without enough D3, your body pulls calcium from bone to keep blood levels stable, which weakens the skeleton over time.
Doctors generally consider a serum 25(OH)D level of 50 to 125 nmol/L (20 to 50 ng/mL) optimal for bone health, according to a state-of-the-art review of vitamin D outcomes. D3 also raises blood levels of 25(OH)D more reliably than vitamin D2, which is why the NIH Office of Dietary Supplements recommends D3 for most supplementation purposes.
The clinical trial data backs this up in a specific way:
- Daily doses of 800 to 1,000 IU of D3, combined with 1,000 mg of calcium, reduced fracture risk modestly in older adults, per the same review.
- That benefit shows up most clearly in people who started out deficient, not in those already replete.
- Correcting a diagnosed deficiency, rather than blanket high dosing, is what the data actually supports.
Vitamin K2 MK-7 vs MK-4: Why the Form You Choose Matters
Vitamin K2 activates two proteins, osteocalcin and matrix Gla protein (MGP), that act like traffic directors for calcium. Once carboxylated by K2, osteocalcin helps bind calcium into the bone matrix, and MGP blocks calcium from depositing in arterial walls. A review of vitamin K2's cardiovascular and bone effects found that higher intake of long-chain menaquinones correlated with meaningfully less arterial calcification and lower cardiovascular mortality over years of follow-up in cohort data.
Not all K2 is equal. The two forms sold as supplements, MK-7 and MK-4, behave differently in your body:
- MK-7 has a longer half-life and stays measurable in the blood for up to 48 hours after a single dose, according to a bioavailability comparison study.
- MK-4, at typical nutritional doses, often failed to raise serum MK-4 levels at all in that same study, requiring milligram-range dosing to have any measurable effect.
- MK-7's pharmacokinetics make once-daily microgram dosing practical, which is why most combined D3+K2 supplements on the market use MK-7 rather than MK-4, a preference formulators confirm directly.
If you're comparing labels, this difference explains why one product lists "45 mcg" and another lists "1.5 mg." They're not comparable doses of the same thing.
The D3 K2 Synergy: How the Two Vitamins Work as a Team
D3 and K2 don't just coexist in a supplement bottle. They work in sequence. D3 raises production of vitamin K–dependent proteins, including osteocalcin and MGP, but those proteins stay inactive (undercarboxylated) without enough K2 around to carboxylate them. Supplementing D3 alone in a K2-poor state can theoretically leave more uncarboxylated MGP circulating, a concern some researchers raise as a rationale for pairing the two nutrients in higher-risk patients, per a review of D and K synergy.
Here's the sequence and what it produces in practice:
- Production step: D3 raises intestinal calcium absorption and stimulates the liver and bone cells to produce more vitamin K–dependent proteins.
- Activation step: K2 carboxylates those proteins, switching osteocalcin and MGP into their active, calcium-directing forms.
- Bone outcome: Multiple randomized trials in postmenopausal women found that combined D+K improved bone mineral density at some skeletal sites and lowered uncarboxylated osteocalcin compared with D3 alone, though sample sizes were often small.
- Vascular outcome (emerging): Some cohort studies and small randomized trials suggest MK-7 supplementation may reduce arterial calcification progression in select populations, though this evidence is far less mature than the bone data.
The bone effect is the better established of the two. The vascular effect is a plausible, biologically consistent signal, not yet a proven outcome across broad populations.
What Clinical Trials Actually Show, and Where They Fall Short
The strongest evidence for D3+K2 supplementation comes from trials targeting people who were already deficient or at elevated risk, not the general population. That distinction shapes almost everything else in this section.
On the positive side:
- Fracture risk fell by roughly 8 to 12% with 800 to 1,000 IU D3 plus 1,000 mg calcium daily in older adults, concentrated among those with low baseline vitamin D.
- The Rotterdam Study, a long-running cohort, linked higher dietary intake of long-chain menaquinones (the K2 family) with reduced arterial calcification and lower cardiovascular mortality over 7 to 10 years of follow-up.
- Several D+K trials in postmenopausal women showed improved bone density measures alongside reduced uncarboxylated osteocalcin, a marker of better K2 activation status.
On the limiting side, large megatrials tell a more sobering story. VITAL, ViDA, and D2d, combined trials enrolling more than 30,000 participants, found no clear benefit of vitamin D supplementation for cancer, cardiovascular events, or type 2 diabetes in adults who already had adequate vitamin D status, according to the state-of-the-art review. Many D+K studies also lean on surrogate markers like bone density or uncarboxylated osteocalcin rather than hard outcomes like actual fractures or heart attacks, and calcium co-supplementation muddies which nutrient deserves credit for the benefit.
The practical read: joint D3+K2 supplementation has the clearest rationale when a real deficiency or elevated fracture or calcification risk is already present, not as a blanket wellness measure for everyone.
How to Dose D3 and K2: Ranges, Timing, and Safety Checks
Getting the dose right matters more than picking a fancy formula. Here's how an individualized clinical approach can work in practice.
- D3 maintenance dosing typically runs 600 to 2,000 IU per day depending on your baseline level and sun exposure; older adults often use 800 to 1,000 IU alongside 1,000 mg of calcium, matching the trial data above. Correcting a diagnosed deficiency usually calls for a higher, clinician-directed regimen rather than an over-the-counter guess.
- K2 (MK-7) dosing in supplements typically runs 90 to 200 mcg per day; intervention trials have used doses from 45 to 360 mcg depending on the outcome studied, per a formulator's dosing FAQ. MK-4, by contrast, often needs milligram-level dosing multiple times a day to move biomarkers, which is far less practical for daily use.
- Timing: Both D3 and K2 are fat-soluble, so take them with a meal that contains some fat for better absorption. MK-7's long half-life makes once-daily dosing realistic; MK-4's short half-life does not.
- Safety review: Check your total calcium intake from food and supplements before adding more, and if you take warfarin or another vitamin K antagonist, talk to your clinician before starting K2, since vitamin K can blunt the drug's effect, per guidance on K2 and blood thinners.
Pro Tip: If you're already tracking calcium intake for bone health, use a calcium dosage calculator before adding a D3+K2 supplement, so you don't accidentally stack calcium sources past a safe daily total.
Unsupervised high-dose D3 (well above maintenance ranges) isn't something to self-prescribe. Get your levels checked first.
Who Should Test Before Supplementing, and Who Should See a Clinician
Not everyone needs a baseline blood test before starting a modest daily D3+K2 supplement, but several groups genuinely should. Older adults at elevated fracture risk, people with limited sun exposure or darker skin, anyone with a malabsorption condition, and patients with chronic kidney disease or prior arterial calcification all fall into that higher-priority group.
If your vitamin D status is unknown, or you're considering a higher-than-maintenance dose, a baseline serum 25(OH)D test gives your clinician real numbers to work from instead of a guess. If fracture risk is a live concern, a bone density test adds another layer of useful information.

From there, a clinician can review your medications (especially anticoagulants), adjust your dose based on lab results, and, when appropriate, refer you into a structured bone health program rather than leaving you to dose by trial and error.
Does D3 K2 Affect Immune Function and Autoimmune Risk?
Vitamin D receptors sit on immune cells throughout the body, including T cells and macrophages, and D3 appears to help regulate how aggressively those cells respond. Deficient vitamin D status has been observed alongside higher rates of several autoimmune conditions in population studies, which has fueled interest in D3's role as an immune modulator rather than just a bone nutrient.
The honest picture, though, is one of correlation more than proven prevention. Low vitamin D shows up often in people with autoimmune disease, but that doesn't establish that correcting the deficiency prevents the disease from developing in someone who doesn't have it yet. The large-scale VITAL trial, one of the most rigorous vitamin D megatrials run to date, found no significant reduction in autoimmune disease incidence from vitamin D supplementation in vitamin-D-replete adults over its study period.
K2's role here is far less studied than D3's. Its established job is directing calcium, not modulating immune cells, so claims about K2 and autoimmune prevention outrun the current evidence.
What this means practically: if you have a family history of autoimmune disease or symptoms suggesting one, correcting a documented vitamin D deficiency is reasonable and evidence-supported for bone and overall health. Treating D3 as a stand-alone autoimmune prevention strategy for someone who isn't deficient is not something the current trial data backs up.
Can Vitamin D3 K2 Improve Mood and Cognitive Function?
Vitamin D receptors are present in brain regions involved in mood regulation, and observational studies consistently find lower vitamin D levels in people with depressive symptoms. That pattern has held up across many population studies, but interventional trials correcting deficiency haven't consistently shown mood improvement as a direct result.
The relationship likely runs in more than one direction. People with depression often spend less time outdoors, which lowers vitamin D production from sunlight, so the low levels may partly reflect the condition rather than cause it. That doesn't make correcting a real deficiency pointless. It does mean vitamin D3 shouldn't be framed as an antidepressant.
Cognitive function research follows a similar shape. Some cohort studies link low vitamin D status with faster cognitive decline in older adults, but randomized trials testing supplementation for cognitive outcomes have produced mixed results. Vitamin K2's role in brain health is even less established; its clearest job remains calcium regulation in bone and vasculature, not neurotransmission.
If you're dealing with low mood or notice cognitive changes, checking vitamin D status is a reasonable, low-risk step, particularly if you have limited sun exposure or another risk factor for deficiency. Just don't expect a supplement to substitute for a full evaluation of mood or cognitive symptoms with your primary care provider.
Vitamin D3 K2 and Metabolic Health: Insulin Sensitivity and Diabetes Risk
Vitamin D receptors exist in pancreatic beta cells, the insulin-producing cells, which has led researchers to study whether correcting deficiency improves blood sugar control. Observational data links low vitamin D status with higher rates of insulin resistance and type 2 diabetes, a pattern seen consistently across large population studies.
The interventional evidence is less encouraging for broad use. The D2d trial, one of the largest randomized trials designed specifically to test vitamin D for diabetes prevention, found no significant reduction in progression to type 2 diabetes among vitamin-D-replete adults with prediabetes, according to the state-of-the-art review. That result mirrors what showed up for cardiovascular events and cancer in the same class of megatrials: correcting deficiency helps people who are actually deficient, but supplementing people who already have adequate levels doesn't appear to move the needle on diabetes risk.
Vitamin K2's connection to metabolic health is newer territory, with some smaller studies exploring whether it influences insulin sensitivity through effects on osteocalcin, which has hormone-like activity affecting glucose metabolism in animal models. Human data here remains preliminary, so it's worth treating with appropriate caution rather than as an established benefit.
If you have prediabetes or a family history of type 2 diabetes, checking your vitamin D status is reasonable, especially if other risk factors for deficiency are present. It shouldn't replace standard diabetes prevention measures like diet, activity, and weight management, which have far stronger evidence behind them.
Why Taking D3 and K2 Together Beats Either Alone
The case for combining these two vitamins rests on a simple mechanical fact: D3 increases production of calcium-regulating proteins, but those proteins need K2 to actually function. Taking D3 without adequate K2 can theoretically leave more of those proteins in their inactive, uncarboxylated form, a concern the D+K synergy review raises as the biological rationale for pairing the two.
Trial data backs this up specifically for bone outcomes. Combined D+K supplementation improved bone mineral density at some sites and reduced uncarboxylated osteocalcin more than D3 given alone in multiple studies of postmenopausal women. That's a meaningfully different result than vitamin D monotherapy trials, which show smaller or less consistent bone density gains.
The cardiovascular case for combination therapy is real but earlier stage. Cohort data on menaquinone intake and reduced arterial calcification is compelling, but there isn't yet a large randomized trial testing D3+K2 together against hard cardiovascular endpoints like heart attack or stroke. Formulators and researchers alike point to K2's role in activating MGP as the plausible mechanism, but plausible mechanism and proven outcome are two different things.
For someone deciding between a D3-only supplement and a combined D3+K2 product, the bone health data alone makes a reasonable case for the combination, particularly for postmenopausal women or anyone with elevated fracture risk. The cardiovascular angle adds supporting rationale without yet being a stand-alone reason to supplement.
Garden State Medical Group's Take on D3 and K2 Supplementation
We favor individualized, evidence-based dosing over one-size-fits-all supplement stacks. Testing your baseline vitamin D status before starting therapy, and reviewing your medication list for anything that interacts with vitamin K, gives you a plan built around your actual numbers rather than a label's suggested serving size.
— Garden State Medical Group
Get Tested Before You Supplement
Guessing your dose from a supplement label isn't the same as knowing your actual numbers. Garden State Medical Group's Bone Health and Vitality Program starts with real diagnostic data, not assumptions, so your D3 and K2 plan is built around your labs, your medications, and your fracture risk rather than a generic recommendation.
If you don't know your vitamin D status, a baseline test through our radiology and diagnostic services settles that question, and a bone density test can clarify your fracture risk if that's a concern. For patients already on warfarin or another blood thinner, a visit with primary care is the right first step before adding any K2 product. Once your plan is set, our professional-grade supplements dispensary carries clinician-recommended D3 and K2 formulations rather than leaving you to sort through drugstore shelves. Schedule an appointment online or through telemedicine to get your testing started.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Vitamin D and Health Outcomes: State-of-the-Art Review (PMC8609267)
- NIH Office of Dietary Supplements — Vitamin D (Health Professional Fact Sheet)
FAQ
Can you take vitamin K2 and D3 every day?
Yes, daily D3 and K2 supplementation is standard in most studied protocols, typically 800 to 2,000 IU of D3 with 90 to 200 mcg of MK-7 daily, though your specific dose should reflect your baseline blood levels.
Should I take D3 plus K2 in the morning or at night?
Timing of day doesn't matter as much as taking both with a meal containing some fat, since they're fat-soluble and absorb better that way.
What is taking vitamin D3 and K2 good for?
The combination is best supported for bone health, helping direct calcium into bone and improving bone density markers in at-risk groups, with emerging but less conclusive evidence for reduced arterial calcification.
Does vitamin K2 reduce belly fat?
No strong clinical evidence supports vitamin K2 for fat loss; its established role is activating proteins that regulate calcium in bone and blood vessels, not fat metabolism.
Is it safe to take D3 and K2 if I'm on blood thinners?
Talk to your clinician before starting K2 if you take warfarin or a similar vitamin K antagonist, since vitamin K can reduce the drug's effectiveness.